Does Medicare Cover Robotic Knee Replacement? Costs, Coverage Rules, and What Surprises Patients
-
September 26, 2026

Reviewed by Emily Horne
Medicare Agent Licensed in OK, AL, AR & 22 other states
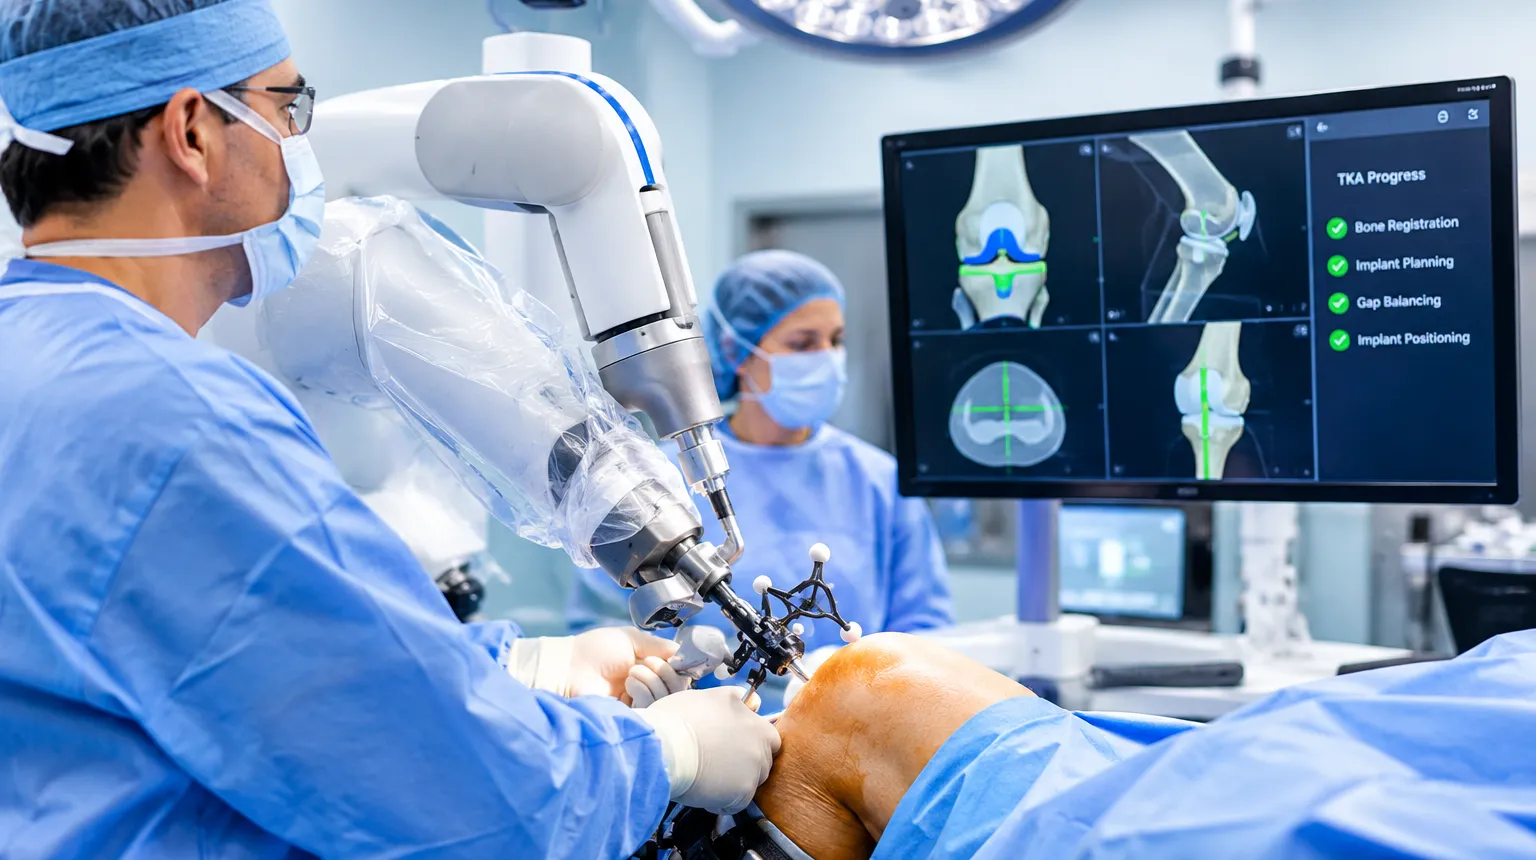
Short answer: yes, Medicare covers robotic-assisted knee replacement surgery, and it pays at the same rate as a traditional knee replacement. There is no separate Medicare billing code that pays the surgeon or hospital extra for using a robot. What changes is where the surgery happens, which plan you carry, and whether your Medicare Advantage plan requires prior authorization before the operating room door opens.
That last piece trips up a lot of patients. A surgeon recommends the robotic approach, the hospital schedules the surgery, and then a call comes a week before the date saying the plan needs additional documentation. This article walks through the coverage rules so you know what to expect on the front end.
How Medicare Pays for Knee Replacement Surgery
The Centers for Medicare & Medicaid Services classifies total knee arthroplasty (TKA) and partial knee arthroplasty (PKA) the same regardless of whether the surgeon uses a robotic system like Mako, ROSA, or VELYS. The robot is a tool, not a separate procedure. So coverage is determined by:
- Medical necessity. Your doctor has to document significant arthritis, joint damage, or pain that has not responded to conservative treatment.
- Site of service. Inpatient hospital stays fall under Medicare Part A. Outpatient knee replacement (which has become much more common since 2018) falls under Medicare Part B.
- Provider participation. The surgeon and facility must accept Medicare.
If your surgery is performed as an inpatient stay, Part A pays the hospital. If it is performed as outpatient or in an ambulatory surgical center, Part B pays. This single distinction is the biggest driver of what you actually owe.
Inpatient vs. Outpatient: Why It Matters
Hospitals classify many knee replacements as outpatient procedures even when the patient stays overnight. That sounds counterintuitive, but Medicare's two-midnight rule determines the classification, not the bed you sleep in. If your surgeon does not expect you to need two midnights in the hospital, the stay is billed under Part B even if you end up staying one night for observation.
Why does this matter? The cost-sharing structures are completely different:
- Part A (inpatient): A single $1,676 deductible in 2026 covers your share for the first 60 days. After that, daily coinsurance kicks in.
- Part B (outpatient): You pay the $257 annual Part B deductible plus 20% of the Medicare-approved amount for surgeon fees, anesthesia, the facility fee, and any related outpatient services — with no cap on that 20% unless you have a Medigap plan.
For a knee replacement with a sticker price around $30,000-$50,000, that 20% coinsurance under Part B can run several thousand dollars out of pocket on Original Medicare alone.

Does Medicare cover hospital observation stays, and how is that different from being admitted as an inpatient?
Yes, Medicare covers hospital observation under the outpatient benefit. If you have Original Medicare that would be Part B services. If you have an Advantage Plan it is charged under outpatient services. Observation means they expect you to be there less than 48 hours. If the hospital admits a patient, they expect a patient to be there more than 48 hours.Robotic-Assisted Surgery: What's Different About the Billing
Surgeons promote robotic knee replacement for the precision of the bone cuts and the personalized alignment based on a pre-op CT scan or intra-op mapping. The clinical case is real, but Medicare doesn't reimburse the hospital extra for the robotic component. The facility absorbs the cost of the equipment and consumables. Patients should know:
- You will not see a separate "robot fee" on your Medicare summary notice.
- The surgeon's professional fee is identical whether the cut is freehand or robot-assisted.
- If a clinic asks you to pay an additional out-of-pocket fee for the robotic technique, that is not something Medicare covers. Ask for the specific billing code in writing before you sign anything.

I'm interested in a robotic knee replacement surgery that my surgeon recommends for my specific anatomy. How does Medicare coverage work for this advanced procedure?
Original Medicare: Medicare premium $185/mo, $257 deductible + (20% of $20,000 to $40,000 + post care costs)$5-10K no max out of pocket.
Medigap Plan G: $200-225/mo+
Medicare premium $185/mo, $257 deductible is your max out of pocket for the year
Medicare Advantage: Medicare premium $185/mo (may be reduced by up to $174,70/mo) specialist copay $10-$45+ outpatient hospital copay $100-$300 + post op rehab $20-$40/visit maximum out of pocket could be less than $500. Max out of pocket $1000-$6700.
The Pre-Op CT Scan
Most robotic systems require a pre-operative CT scan to build a 3D model of your knee. That scan is billed separately under Part B. You'll owe the standard 20% coinsurance after your deductible unless you have supplemental coverage. The scan typically runs a few hundred dollars in Medicare-approved charges.
What Original Medicare Pays vs. What You Pay
Here is a realistic breakdown for a Medicare-approved robotic knee replacement performed as an outpatient procedure in 2026, assuming a $35,000 total approved amount across surgeon, facility, anesthesia, and pre-op imaging:
- Part B annual deductible$257
- 20% coinsurance on approved charges~$6,950
- Physical therapy (typically 12-24 sessions, 20% each)~$400-$800
- Durable medical equipment (walker, ice machine)~$50-$200
- Estimated patient share$7,600-$8,200
If the surgery is classified as inpatient and Part A applies instead, your hospital cost-sharing drops to the $1,676 deductible for the stay itself — but the surgeon's fee, anesthesia, and follow-up care still bill under Part B, so the 20% coinsurance on those items still applies.
This is why most Medicare beneficiaries who go through joint replacement carry a Medigap plan or a Medicare Advantage plan. The exposure on Original Medicare alone is real, and it has no annual cap.
How Medigap Changes the Math
A Medicare Supplement (Medigap) plan pays the gaps Original Medicare leaves behind. For knee replacement specifically:
- Plan G covers everything after you pay the small annual Part B deductible. Your out-of-pocket on a $35,000 robotic knee replacement could be as little as $257.
- Plan N covers most gaps but leaves you a copay (up to $20 for office visits, up to $50 for ER) and Part B excess charges. For a major surgery your share is still well under $500 in most cases.
- High-Deductible Plan G requires you to meet a $2,870 deductible first (2026), then covers the rest. Often the right pick for people who don't expect heavy claims most years but want catastrophic protection.
Choosing among supplements is a real decision, not just a price comparison. For a fuller look at when Plan N or High-Deductible G can beat the more popular Plan G, see when Plan N, Plan K, or High-Deductible G actually beats Plan G.

I'm on Medigap Plan G, and I'm curious how my upcoming knee replacement surgery will be billed. Does the plan cover it all after my deductible?
Yes. As long as the facility where you have the surgery accepts Medicare assignment, you will only be responsible for the Part B annual deductible ($257 for 2025). Once you pay the Part B annual deductible, Medicare will pick up 80% of the remaining bill, and your Medigap Plan G will pick up the other 20%.What If You Don't Have a Medigap Plan Yet?
If you are inside your six-month Medigap Open Enrollment Period (the window that begins when you are 65 and enrolled in Part B), you can buy any Medigap plan sold in your state with no health questions asked, including planned knee surgery. Once that window closes, most states allow insurers to medical-underwrite, and a surgery on the calendar will make underwriting difficult.
A small group of states have birthday rule or continuous open enrollment protections that change this. If you live in one of those states, switching Medigap plans without underwriting may be possible. A local agent can confirm what your state offers. You can find a licensed Medicare agent who works with multiple Medigap carriers to compare what's available.
Medicare Advantage and Robotic Knee Replacement
Medicare Advantage (Part C) plans must cover everything Original Medicare covers, which means yes, your MA plan will cover a medically necessary robotic knee replacement. But the experience is different from Original Medicare in three important ways:
- Prior authorization is almost guaranteed. Most MA plans require pre-approval for joint replacement surgery. Your surgeon's office submits records and a plan of care, and the insurer reviews medical necessity. Approval usually comes through, but denials and delays happen — sometimes within days of the scheduled date.
- Network rules apply. If your preferred surgeon or hospital is out of network, the plan may not cover the surgery, or will cover a smaller share. HMO plans are stricter than PPO plans on this.
- Cost-sharing is set by the plan, not Medicare. You'll likely have a daily inpatient hospital copay, an outpatient surgery copay, and an annual out-of-pocket maximum (capped at $9,350 in 2026 for in-network services on most MA plans).

I called to ask about a knee replacement and suddenly they said I need prior authorization. I thought my plan was supposed to be good-what's going on?
If you have a Medicare Advantage plan thy could ask for a prior authorization. It also could depend on the healthcare provider, or weather it is an HMO or a PPO.If your plan denies coverage for the robotic procedure or for any portion of the surgical care, you have appeal rights at multiple levels. The process is well-defined but it requires fast action — most appeals must be filed within 60 days. See how to appeal a denied Medicare claim for the step-by-step.
Recovery: What Medicare Pays For After Surgery
The hospital bill is only part of the cost. Most knee replacement patients need a few weeks of structured rehab. Medicare covers:
- Physical therapy under Part B, with 20% coinsurance after the deductible. There is no longer a hard cap on PT visits, but services beyond a certain dollar threshold require your therapist to document continued medical necessity.
- Home health care if you are homebound after surgery and your doctor orders it. Part A or Part B pays depending on the situation; you generally pay nothing for covered home health services.
- Durable medical equipment like a walker, cane, raised toilet seat, or knee CPM machine when prescribed. Part B pays 80% after the deductible.
- Skilled nursing facility stay if you had a qualifying inpatient hospital stay of at least three days. Days 1-20 are fully covered; days 21-100 carry a daily coinsurance ($209.50 in 2026).
The three-day inpatient rule is where outpatient classification can come back to bite you. If your knee replacement was classified as outpatient, you may not qualify for Medicare-covered SNF rehab afterward. Ask the hospital case manager about your admission status before discharge — it directly affects what comes next.
Practical Steps Before You Schedule
- Confirm in writing whether the surgery is being billed as inpatient or outpatient. This is the single biggest factor in your out-of-pocket cost.
- Ask your plan (MA or Medigap) for a written cost estimate based on the CPT codes the surgeon's office plans to bill. Most plans will provide this.
- Get prior authorization in writing before the surgery date if you have Medicare Advantage. Don't rely on verbal approvals from the surgeon's office.
- Verify network status for the surgeon, the hospital, the anesthesiologist, and any pre-op imaging facility. Out-of-network anesthesia is a common surprise bill on Medicare Advantage.
- If you're new to Medicare, understand how supplements fit into the picture. Medicare choices at age 65 walks through the key decisions.
Where a Local Agent Helps
Most beneficiaries pick their Medicare plan once and don't revisit it until a major medical event forces the question. A robotic knee replacement is one of those events. If your current plan leaves you with five-figure exposure or requires you to use a hospital you don't want to use, a Medigap shop or a Medicare Advantage plan switch during the next enrollment window might save you significant money — or get you to the surgeon you actually want.
A local independent agent who works with multiple carriers can run plan comparisons against your specific surgeon, hospital, and medications. There is no cost to you; agents are paid by the insurance company once you enroll. Browse the how Medicare Supplement agents help page to see what an agent actually does for clients facing surgery decisions.
The Bottom Line
Medicare covers robotic-assisted knee replacement on the same terms as a traditional one. The robot itself is not a coverage question. The real questions are whether your surgery is classified as inpatient or outpatient, whether you have a Medigap plan that absorbs the 20% Part B coinsurance, and whether your Medicare Advantage plan has cleared prior authorization for the procedure, the surgeon, and the facility. Get those three pieces locked down in writing before surgery day, and the financial side of recovery becomes a non-event.