Dialysis Makes You Medicare-Eligible at Any Age, But Coverage Starts in Month 4
-
October 9, 2026

Reviewed by Morgan Honea
Medicare Agent Licensed in NM, AL, AR & 42 other states
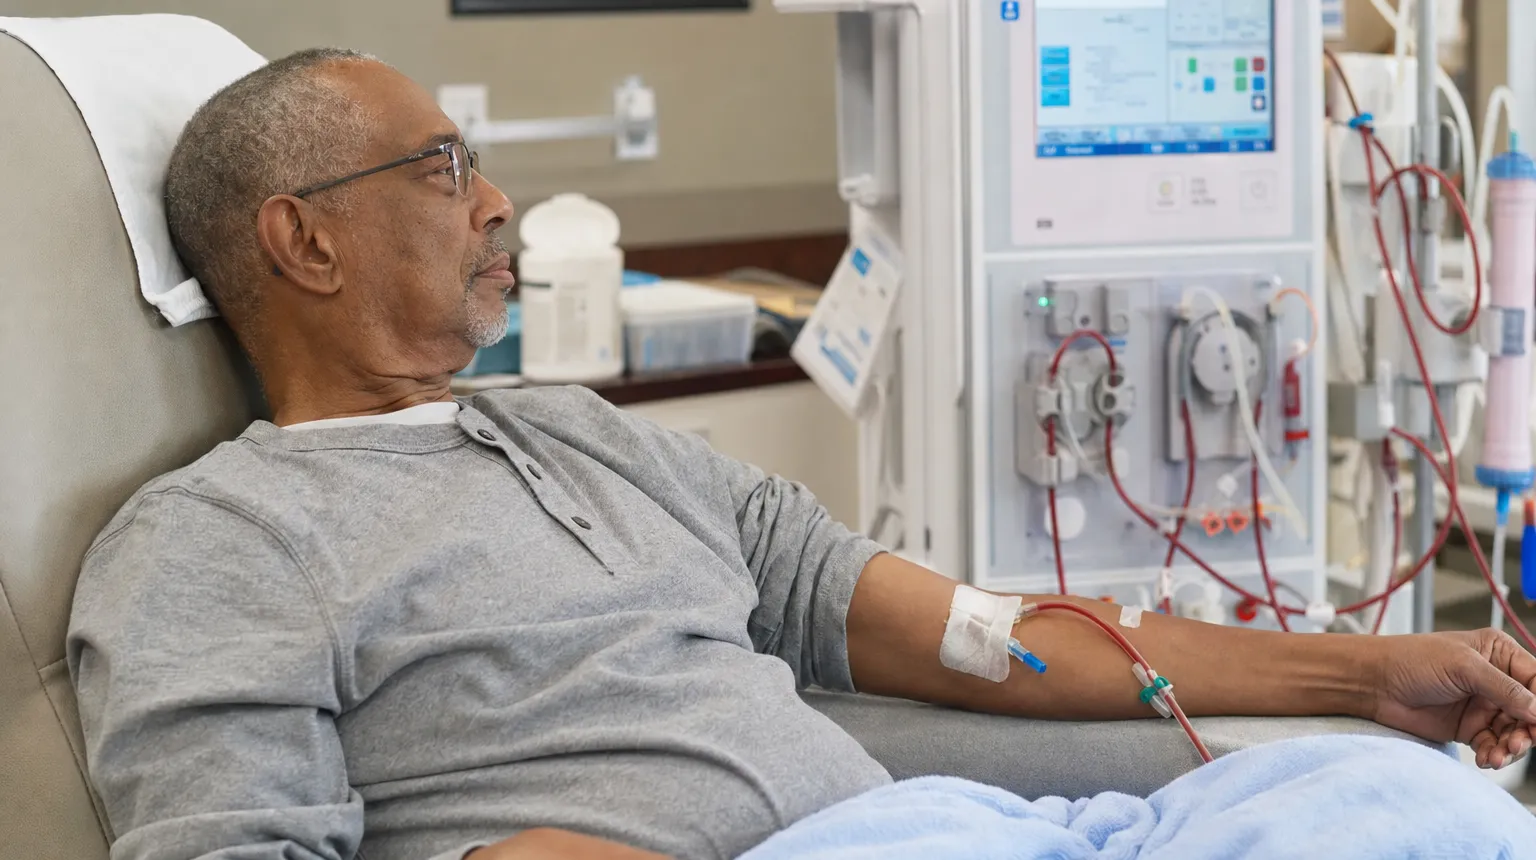
If you start dialysis for kidney failure, you qualify for Medicare at any age. You could be 34 or 54. Age stops mattering the moment permanent kidney failure enters your chart.
What catches families off guard is the calendar. Eligibility and coverage are two different things, and for most people starting in-center dialysis, Medicare does not pay a dime until the first day of the fourth month.
Quick answer: End-Stage Renal Disease (ESRD) qualifies you for Medicare regardless of age, but coverage usually begins on the first day of the fourth month of dialysis. Start a home dialysis training program before the end of month 3 and that wait can disappear. Whatever insurance you already have pays during the gap, and it keeps paying first for 30 months after that.
Dialysis is one of the few doors into Medicare before 65
There are three common ways to get Medicare early: 24 months of Social Security disability payments, an ALS diagnosis, or ESRD. Kidney failure is the only one of the three tied to a treatment schedule rather than a benefit clock.
Agents describe the ESRD path as the rare one with no 24-month disability wait attached. You still need the work history, either your own or a spouse's or parent's record, and you still have to apply the way any under-65 beneficiary does. Medicare does not show up automatically because a nephrologist wrote an order.

Who qualifies for Medicare coverage if they are under 65?
People under 65 can qualify for Medicare if they receive Social Security Disability Insurance (SSDI) for 24 months or have received Railroad Retirement Board disability benefits. The 24‑month waiting period does not apply to individuals with Amyotrophic Lateral Sclerosis (ALS, “Lou Gehrig’s disease”), who become eligible for Medicare as soon as they receive SSDI (no waiting period). Additionally, individuals with End‑Stage Renal Disease (ESRD) may qualify if they require regular dialysis or have had a kidney transplant and meet certain work and insurance requirements.That application piece trips people up. Several agents pointed out that you sign up through Social Security, either at a local office or through your SSA account, and that you need both Part A and Part B to get the full benefit. Part A alone covers the hospital side. Dialysis itself lives in Part B.
One useful detail buried in the answers: coverage can be backdated as far as 12 months before you apply. If you started dialysis last spring and are only now filing, ask about retroactive entitlement.
The fourth-month rule, and the home training loophole that erases it
For in-center hemodialysis, the standard is three full months of treatment, then Medicare starts on day 1 of month 4. If you began treatment in January, your card works in April.
The exception is worth real money. If you enroll in a home dialysis training program before the end of that third month, coverage can start with the first month of dialysis instead. Agents repeated this one more than any other technical point in the entire answer set, which tells you how often it gets missed at the clinic.

If I start dialysis, how does that change my Medicare eligibility or coverage?
Typically, your coverage begins on the first day of the fourth month of continuous dialysis. There is an exception for home dialysis, which can allow coverage to start sooner, but you have to enroll in the home training program.In-center dialysis:
Your coverage typically starts on the the first day of the fourth month of dialysis.
Home dialysis:
You can receive Medicare coverage starting on the first day of your first month of home dialysis, provided you begin a home training program before the end of your third month.
Home dialysis is not a workaround invented by agents. Part B covers it directly: the machine, the supplies, the training for you and whoever helps you at home, and the monitoring visits from the dialysis facility. Same 80/20 math, different setting.

Does Medicare cover dialysis at home or in-center?
Medicare covers dialysis both in-center and at home.• In-center dialysis is covered under Medicare Part B.
• Home dialysis is also covered, including the training, equipment, and supplies you need to do it safely.
• Medications related to dialysis are usually covered under Part B or Part D, depending on the drug.
So if home dialysis is medically reasonable for you, ask about the training program in month 1, not month 4. By month 4 the question is moot.
Who pays during the three-month gap
This is where the coverage hole opens. You are eligible. Your card is not active yet. Something has to pay for three months of treatment that can run into five figures.
If you have employer coverage or a commercial plan, it pays. That plan is your primary payer for the entire waiting period, and agents were blunt about the risk if you drop it early. Cancel the group plan the week your nephrologist says "dialysis" and you have bought yourself three uninsured months.

If I start dialysis, how does that change my Medicare eligibility or coverage?
Starting dialysis changes Medicare eligibility and coverage in a few key ways. If you're not already eligible for Medicare, starting dialysis will likely trigger eligibility for Medicare Part A and Part B because of your End-Stage Renal Disease (ESRD). However, your Medicare coverage won't start immediately. There's a waiting period, and your commercial insurance (if you have it) will be primary for the first three months of dialysis.Here's a more detailed breakdown:
Eligibility:
If you haven't already met the typical Medicare age or disability requirements (65 or older, or under 65 with a qualifying disability), starting dialysis will make you eligible for Medicare due to ESRD.
Waiting Period:
If you're under 65 and only eligible for Medicare because of ESRD, your Medicare coverage usually starts on the first day of the fourth month of dialysis. This means your commercial insurance (or any other coverage you have) will likely be the primary payer for the first three months.
Medicare Parts:
You'll need both Medicare Part A (hospital insurance) and Part B (medical insurance) to get the full benefits for dialysis and kidney transplant services. You can also add Medicare drug coverage (Part D).
Medicare Advantage:
While Original Medicare (Part A and B) covers many dialysis-related services, you can also enroll in a Medicare Advantage plan. These plans have different cost-sharing, provider networks, and coverage rules, so it's important to research them carefully.
Coordination of Benefits:
For the first 30 months of your Medicare eligibility, your commercial insurance (if you have one) will be the primary payer for your dialysis treatments. After this period, Medicare will become the primary payer.
If you have no other coverage, this is the moment to talk to the dialysis center's social worker about Medicaid and state assistance. Agents pointed there repeatedly, and most centers have a case manager whose whole job is bridging exactly this gap.
The 30-month coordination period after that
Medicare starting does not make Medicare the primary payer. For 30 months from the date your ESRD-based Medicare eligibility begins, your group health plan pays first and Medicare pays second. Only after those 30 months does Medicare move to the front of the line.
Employer size matters everywhere else in Medicare, and it matters here too. The general rule agents cite is 20 or more employees means the group plan pays first, under 20 means Medicare pays first. ESRD overrides that in its own way, which is why the coordination question is worth asking out loud rather than assuming.

If I have both Medicare and employer health insurance, which one pays first?
If you have both Medicare and employer health insurance, which plan pays first depends primarily on the size of your employer. If your employer has 20 or more employees, your employer health plan generally pays first, and Medicare pays second. If your employer has fewer than 20 employees, Medicare usually pays first, and your employer plan pays second.Because coordination of benefits can vary based on your specific situation, it's important to review your coverage before delaying Medicare enrollment or relying solely on employer insurance.
Practical effect: keeping the employer plan during those 30 months is usually the right call, and the handoff from employer coverage to Medicare should be planned rather than improvised.
ESRD-based Medicare can end. Two clocks to watch
If ESRD is your only ticket into Medicare, meaning you are under 65 and not on disability, your coverage is conditional. It runs out.
- 12 months after the month you stop dialysis
- 36 months after a successful kidney transplant
A transplant is the goal of the whole process, and it is also the thing that starts a 3-year countdown on your health insurance. Part B can continue past that point for immunosuppressive drugs in some cases, which matters enormously since those drugs are what keep the new kidney working. Coverage can also come back if dialysis restarts or you hit another qualifying condition.

If I start dialysis, how does that change my Medicare eligibility or coverage?
Starting dialysis for End-Stage Renal Disease (ESRD) makes you eligible for Medicare regardless of your age, as long as you meet the other work history benefit eligibility requirements. It's one of the few conditions allowing Medicare eligibility under 65 without waiting through a disability waiting period.If you’re already on Medicare, starting dialysis doesn't change your eligibility. Your existing coverage starts paying for dialysis services immediately. However, if you're not on Medicare, you become eligible due to ESRD. You must apply through Social Security, coverage can be retroactive up to 12 months before the application.
NOTE: When Coverage Ends (If Only Eligible Due to ESRD)
12 months after the month you stop dialysis.
36 months after a successful kidney transplant.
Part B can continue longer for immunosuppressive drugs in some cases. Coverage can resume if dialysis restarts or other qualifying conditions are met.
If you are 40 with a new kidney, month 36 needs to be on your calendar the day you leave the hospital. That is when you go find employer coverage or a marketplace plan.
The out-of-pocket math that catches dialysis patients
Original Medicare pays 80% of the approved amount for dialysis after the annual Part B deductible. You owe the other 20%, and on Original Medicare alone there is no ceiling on that 20%. Three treatments a week, every week, forever, with no cap.
On a Medicare Advantage plan there is a cap, and it is called the MOOP. Agents were direct about what that means for a dialysis patient: you will hit your maximum out-of-pocket every single year you are on dialysis. How fast depends on your plan and your other care, but you will get there. Then it resets every January and you do it again. Understanding what does and doesn't count toward that limit stops being academic when you are the person paying it.

Can you help me understand Maximum Out-of-Pocket (MOOP) limits in Medicare plans, from your experience as an agent?
The maximum out of pocket is your threshold for copayments and deductibles. After it is met, you go to 100% coverage for the year. My experience as an agent is that shockingly few people ever reach the maximum out of pocket. The reason is because many plans do not have a deductible and the copays are very low. Even hospitalization is not going to be all that high. As a result, the only people I ever see reach it is people that go through very serious chronic conditions like cancer, kidney failure, and others that require so many specialist and high dollar treatments.Which is why so many agents in this data set steered toward a Medicare Supplement instead, since Medigap picks up the 20% and turns an unpredictable year into a fixed premium. The catch is access. Under 65, Medigap availability depends entirely on your state, and in plenty of states the only realistic option is a Medicare Advantage plan. Even at 65 and older, agents warned that once you are on Advantage with a dialysis diagnosis, moving to a supplement later can mean underwriting you may not pass.
Price both. Then decide.
C-SNPs built for kidney patients
Chronic Condition Special Needs Plans are Medicare Advantage plans designed around one condition. There are C-SNPs for diabetes, for heart conditions, and for ESRD specifically.

What are the different types of Special Needs Plans (SNPs) in Medicare?
The main two types of Special Needs Plans are C-SNP and D-SNP.A C-SNP is a Chronic Special Needs Plan. These plans are designed to give extra attention and some extra benefits to beneficiaries with qualifying chronic conditions. The most common conditions are Diabetes, Chronic Heart Failure and Cardiovascular disease. However, each state may have different rules, so check your state.
A D-SNP is a Dual Special Needs Plan. These plans are designed to address the needs of beneficiaries with extremely limited income and resources. These plans may offer additional support in paying Part B and Part D copays and coinsurance as well as offering grocery and utility benefits.
What agents like about them for dialysis patients is the tailoring. Formularies built around the drugs you actually take. Care coordination that comes with the plan instead of something you assemble yourself. Transportation benefits, which matter a lot when the treatment schedule is three round trips a week. And in some markets, dialysis cost sharing at or near $0.
They are not automatically the best answer. C-SNPs are network plans, so your nephrologist, your dialysis center, and your transplant team all need to be in it. Availability is county by county. Some carriers do this well and some do not.

What’s the best Medicare plan for someone with chronic kidney disease?
There really isn’t one single “best” Medicare plan for someone with Chronic Kidney Disease (CKD) because it depends on several important factors like:• Stage of kidney disease
• Current doctors and specialists
• Dialysis needs
• Prescription medications
• Hospital systems being used
• Financial situation and Medicaid eligibility
But there ARE certain things someone with CKD should pay very close attention to when choosing coverage.
For many people with CKD, the biggest areas to review are:
• Dialysis coverage and costs
• Specialist access (especially nephrologists)
• Hospital networks
• Prescription drug coverage
• Transportation benefits
• Maximum Out-of-Pocket exposure
• Access to Special Needs Plans (C-SNPs)
In some cases, a Chronic Condition Special Needs Plan (C-SNP) designed for kidney disease or diabetes can provide additional benefits, care coordination, lower costs, and support services.
Others may prefer Original Medicare with a Medicare Supplement because it can offer more provider flexibility and predictable costs.
The important thing is this:
A plan that works great for a healthy person may be a terrible fit for someone managing CKD.
That’s why I always encourage people to review the FULL picture — doctors, medications, dialysis centers, hospitals, and overall financial exposure — not just the premium.
I help seniors and families compare these options every day and explain things in plain English so they can make informed decisions and avoid costly surprises — always at no cost.
Chuck Winslow
US Marine Veteran 🇺🇸
Retirement & Legacy Planner
Contact me.
There is one point where agents genuinely disagree, and it is worth knowing before you call anyone. Some say an ESRD diagnosis opens a special election period to move into a plan with kidney-specific benefits. Others say that if you are already on Medicare, nothing opens until the fall Annual Enrollment Period. Ask a licensed agent to check your specific situation rather than assuming a mid-year switch is available. It sometimes is. It is not guaranteed, and a new diagnosis by itself usually doesn't create an enrollment window.
What to do in your first month of dialysis
- Apply through Social Security for Part A and Part B. Do not wait for month 4. The application is what starts everything.
- Ask about home dialysis training this month. If it is a fit medically, it can pull your start date forward by three months.
- Do not cancel your current insurance. It is your primary payer through the gap and for 30 months after.
- Talk to the center's social worker about Medicaid, state programs, and any grant assistance. That conversation is free and plenty of people never have it.
- Get a plan comparison from an independent agent before your card activates, covering Medigap if your state allows it under 65, standard Advantage plans, and any ESRD C-SNP in your county.
Dialysis changes almost everything about a life. The insurance piece is one of the few parts of it you can get ahead of, and the window to do that is the first three months.
If you want someone to run the numbers for your county, your nephrologist, and your medication list, you can find a licensed Medicare agent who works your area. Reading through what dozens of agents said about dialysis and Medicare eligibility is a decent place to start too.